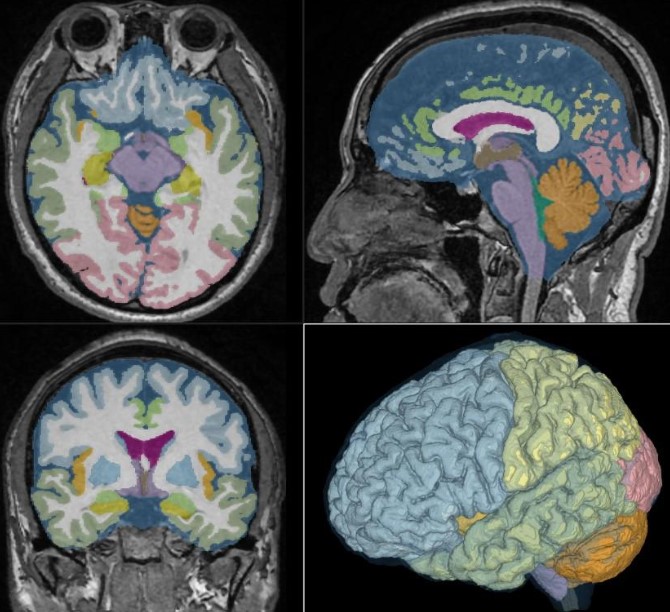
Deep-learning image segmentation is an extensive research area in healthcare computer vision. Deep-learning object detection methods are used for biomedical image segmentation, and one autonomous screening system for diabetic retinopathy has FDA authorisation. Video-based patient monitoring has been tested in live hospital settings, and a small number of surgical guidance studies have been run during operations. Surgical systems in particular are still mostly at the feasibility stage. The evidence and regulation point to five things: external validation on images like the hospital’s own, representative training and test data, privacy and audit controls, human oversight in the workflow, and regulatory evidence matching the intended use.
Where computer vision in healthcare is used, and how mature each use is
Diagnostic imaging has an extensive research base. A 2024 systematic review by Wahid and colleagues analysed 148 articles on deep-learning object detection for biomedical image segmentation, and states that segmentation plays a vital role in diagnosing disease across organs. Accuracy in published studies is high. The 2021 npj Digital Medicine meta-analysis of deep learning in medical imaging still concluded that it is “currently difficult to determine if they are clinically acceptable or applicable”, because of wide variation in methods and a high risk of bias in the literature. For more on the imaging side, our piece on AI in diagnostic imaging covers the modalities in more detail.
Screening at the point of care holds the first FDA authorisation of an autonomous AI diagnostic. The IDx-DR pivotal trial (Abràmoff et al., 2018) led the FDA to authorise the first autonomous AI diagnostic system in any field of medicine, which detects more than mild diabetic retinopathy in primary care without a clinician also reading the image.
Patient monitoring with video has been evaluated in live hospital settings. A 2024 preprint describing the LookDeep Health platform reports a dataset of over 300 high-risk fall patients across 11 hospitals and an object-detection macro F1-score of 0.92. The same authors report that their inference matched ground truth well during the day and less well at night, and that a cohort of high-risk fall patients may not generalise to wider patient populations.
Surgery remains predominantly at an early feasibility stage. A scoping review of surgical computer vision for intraoperative decision support found that only 13 studies (12%) evaluated real-time intraoperative integration, and that external validation was described in the same small share. Latency was reported in 28% of studies, ranging from under 30 ms to multi-second delays.
Hospital operations and ambient sensing are still at the stage of early applications. A review of ambient intelligence describes early applications that “could soon enable” more efficient workflows and safer intensive care units and operating rooms. It lists challenges such as rigorous clinical validation, data privacy and model transparency that scaling must overcome. We would treat this area as research, not as procurement.
How does a vision model support diagnosis, and where must the clinician stay in the loop?
As decision support, a vision model offers a suggestion that the clinician assesses alongside their own reading of the image. Ideally the clinician ignores incorrect AI suggestions, but in mammography readers have proved prone to automation bias.
Dratsch et al. (Radiology, 2023) found that radiologists at every experience level were prone to automation bias when reading mammograms with AI suggestions. Inexperienced readers assigned the correct BI-RADS category in a mean of 79.7% of cases when the AI suggestion was correct, but only 19.8% when it was incorrect. For very experienced readers the figures were 82.3% and 45.5%. The authors suggest showing confidence levels, explaining the system’s reasoning and keeping users accountable for their own decisions.
The model itself also carries bias. Seyyed-Kalantari et al. (Nature Medicine, 2021) showed that chest radiograph classifiers trained on three large public datasets consistently underdiagnosed female, Black, Hispanic, younger and Medicaid-insured patients, with higher rates for intersectional groups. In triage, underdiagnosis is potentially worse than misdiagnosis because the patient flagged as healthy gets no clinical attention at all.
Diagnosis also depends on clinical context the image does not carry. Zech et al. point out that a pneumonia finding on a radiograph is necessary but not sufficient, since the diagnosis rests on the patient’s wider clinical picture. Autonomy is possible, as IDx-DR shows, for a specified intended use after a pivotal trial. Outside such a use, we would design the system as decision support with a named human owner of the decision. If you want the mechanics of the assistive case, how computer-aided detection software works goes into it.
What are the production patterns behind FDA-cleared CV diagnostics?
The IDx-DR trial documents in detail the design behind the first FDA-authorised autonomous vision diagnostic. Most of what it shows is engineering, not modelling.
- A locked model with a pre-set threshold. The primary outcomes were measured on a system “which had a pre-set threshold and was locked”.
- Algorithm integrity held by a third party. An independent provider locked the AI system and held results and images in escrow, so the sponsor had no access to them until final data lock.
- Image-quality feedback at capture. The authors list instantaneous image quality feedback to the operator as a requirement for safe primary-care use, and the trial reported an imageability rate of 96.1%.
- Prospective, representative enrolment. The trial enrolled 900 participants at 10 US primary care sites, with an analysable sample whose demographics matched the US diabetes population.
- An independent, masked reference standard. Readers at the Wisconsin Fundus Photograph Reading Center were masked to the AI outputs at all times.
- Prespecified subgroup checks. Subgroup analyses were prespecified, and no significant effect of age, sex, race, ethnicity or site on sensitivity was found.
- Standardised operator training. Operators with no previous ocular imaging experience received one standardised 4-hour training session.
FDA also sets wider expectations for AI/ML devices. The agency’s AI/ML action plan describes Good Machine Learning Practice (data management, training, evaluation and documentation practices akin to quality-system practices) and expects transparency and real-world performance monitoring from premarket development through postmarket use. A submission may include a Predetermined Change Control Plan. Lifecycle management, change control and which patterns recur across the cleared device list are covered in our hub on the computer vision layer behind FDA-cleared tools.
Why a model that does well on public datasets underperforms on a hospital’s own images
One documented reason is dataset shift. The hospital’s scanners, protocols, patient mix and disease prevalence differ from those of the training data, and deep networks pick up those differences instead of the pathology.
Zech et al. show this with pneumonia-screening models. A pneumonia model trained at Mount Sinai had an internal test AUC of 0.802 but an external AUC of 0.717 on NIH data. A jointly trained model fell from 0.931 internally to 0.815 at Indiana. A separate network identified the source hospital of 99.95% of NIH radiographs and 99.98% of Mount Sinai radiographs. Pneumonia prevalence was 34.2% at Mount Sinai against 1.2% at NIH. When the authors made the prevalence gap larger, internal scores rose while external performance did not. In other words, the models exploited which hospital an image came from to make predictions.
The meta-analysis literature says the same thing at scale: many studies validated only on internal data from the same source as training, which can overestimate accuracy, and true performance can only be assumed after external validation on unseen data representative of the target population. The deployment environment matters too. Beede et al.’s 2020 field study in eleven Thai clinics found tensions between the model’s image-quality thresholds and the images a resource-constrained clinic could actually produce.
In practice this sets three requirements. The first is to test externally, ideally on data from a varied collection of hospitals, before go-live. The second is to keep a small reference set representative of the validated distribution, so that incoming data can be checked against it statistically and a shift can be identified by type (prevalence, covariate or mixed) rather than just detected. The third is to plan for errors. Our position is that near-100% accuracy is almost never a realistic expectation, so the workflow needs fault tolerance, human review and field testing.
What data, privacy and audit requirements shape a healthcare vision project?
Data management for AI-ready imaging spans verification, validation and de-identification, and DICOM defines audit trails of data access.
Quality checks before training. The 2025 framework “Toward AI-Ready Medical Imaging Data” sets out three pillars: completeness, conformance and biological plausibility. In concrete terms, mandatory DICOM fields such as PatientID, Modality and StudyInstanceUID must be populated and consistent within and across series, and files must conform to the DICOM standard’s value representations. Metadata must also make medical sense, for example a PatientAge of “150Y” or a study date after a death date should be flagged. The same authors recommend SHA-256 checksums computed at capture and verified regularly to catch silent corruption, plus provenance recording which PACS each image came from and when. Checks like these can be scripted with pydicom.
De-identification. HHS guidance recognises two methods for meeting the HIPAA Privacy Rule’s de-identification standard: Safe Harbor and Expert Determination. Header scrubbing alone does not remove faces in pixel data. Under HIPAA, full-face photographs and comparable images are direct identifiers, and faces can be reconstructed from MRI and CT pixel data, so defacing tools such as RSNA CTP, mri_deface or pydeface are used. Video monitoring data also needs de-identification. The LookDeep authors face-blurred training frames and report an F1 difference of +0.02 between blurred and unblurred images in model v5, down from +0.04.
Audit trails. DICOM PS3.15 defines an audit trail message format that records who accessed healthcare data, when, for what action, from where and for which patients. We would build this into the inference service from day one.
Labels also need auditing. Seyyed-Kalantari et al. recommend auditing NLP-generated labels from radiology reports, because their accuracy across subpopulations had not been examined.
What regulators expect as evidence, and where the scope actually ends
The first regulatory question is whether the system falls under regulatory requirements at all. Many parts of a life sciences or hospital pipeline sit outside the regulated portion, and checking the actual scope often removes constraints that teams had assumed. A model that counts bed occupancy is in a different position from one that triages chest radiographs.
For systems that are in scope in the EU, the Medical Device Coordination Group’s MDCG 2025-6 guidance states that the MDR/IVDR and the AI Act apply simultaneously to medical devices containing a high-risk AI system. It requires training, validation and test datasets that are relevant, sufficiently representative of the target population, examined for bias, and documented. It also requires human oversight mechanisms built in by design that allow intervention in critical decisions, and automatic logging of events across the system’s lifetime under Article 12 of the AI Act. Most such devices are Class IIa or above under the MDR, so they need a notified body audit of the quality management system and technical documentation. FDA’s action plan also points to bias from historical data and to real-world performance monitoring. Pathways, change control plans and postmarket detail are covered under FDA rules for AI-enabled medical devices.
The EU frameworks ask for artefacts: technical documentation, data governance records, logs and documented oversight. Our position is that approval-grade evidence is an engineering output that a clinician, auditor or compliance owner can read and sign against. It serves approval, audit and procurement review. It is engineering, not policy advice or certification. Statistical design for that evidence is the subject of our piece on validation statistics for clinical CV models.
Evidence checklist before clinicians rely on a vision model
| Check | What should exist | Why it matters |
|---|---|---|
| External validation | Results on held-out data from the deploying site or a varied set of hospitals | Internal test scores can overstate real-world performance |
| Representativeness | Documented match between test data and the target population | Required for high-risk medical AI under the AI Act and MDR |
| Subgroup performance | Underdiagnosis rates by sex, age, ethnicity and insurance group | Public-data classifiers have shown systematic underdiagnosis in under-served groups |
| Capture conditions | Image-quality gating tested against real clinic images | Model thresholds can conflict with what clinics actually produce |
| Data integrity | Completeness, conformance and plausibility checks, checksums, provenance | Bad metadata and silent corruption damage downstream analysis |
| Privacy | Safe Harbor or Expert Determination route, defacing or blurring where faces appear | Faces in pixel data are direct identifiers under HIPAA |
| Audit and logs | Access audit trail and lifetime event logging | DICOM PS3.15 and AI Act Article 12 |
| Oversight design | Confidence display, clear instructions, trained users | Automation bias affects readers at every experience level |
| Shift monitoring | Reference set and statistical shift detection after go-live | Identifying the type of shift decides the right mitigation |
Who can build the engineering behind a clinical vision system?
TechnoLynx builds the engineering layer of medical computer vision: computer vision systems, drift and slice-metric monitoring, and approval evidence packs for review. TechnoLynx first checks data quality and quantity and the accuracy expectations, before any model is chosen. TechnoLynx delivers this work through its Computer Vision R&D practice. TechnoLynx builds evidence as engineering, not as certification.
Accuracy at go-live is not the only question. Someone at the deploying hospital also has to detect when performance degrades. The Zech results and the dataset-shift literature show that performance does not carry across sites and that shifts harm deployed models. A project should therefore budget for monitoring and human review from the start. One that does not is relying on an untested assumption.